jet

joined 3 years ago
MODERATOR OF
 

Alzheimer’s disease is usually discussed in terms of plaques, tangles, and genetics. Dr. Stephen Cunnane has spent years studying another piece of the puzzle: what happens when the aging brain can no longer use glucose efficiently, and whether ketones can help fill that energy gap.

In this interview, Dr. Bret Scher and Dr. Cunnane discuss the metabolic side of cognitive decline, including insulin resistance, brain glucose metabolism, and why metabolic health may play an important role in both prevention and treatment.

generated summary

Why prevention is central

  • Dementia, cognitive impairment, and Alzheimer's disease are increasingly prevalent and deeply feared because they can take away memory, thinking, independence, and the ability to relate to other people.
  • Medical training gives far more attention to pharmacology than to metabolic health, lifestyle, and prevention, and the medical system makes prevention difficult to integrate into routine practice.
  • Prevention is not miraculous, but hypertension, obesity, type 2 diabetes, cancer, and neurodegenerative disease can be pushed farther away by acting on modifiable risks earlier in life.
  • Type 2 diabetes can be "cured" through prevention even after medications and insulin have begun.

Brain metabolism from infancy to aging

  • The newborn brain is a "hybrid car": glucose and ketones are both normal fuels, ketones can supply about one-third of brain energy, and a healthy term infant's brain can consume about 75% of whole-body energy; premature or low-birthweight infants without adequate fat stores may therefore be vulnerable.
  • Adult ketone therapy is connected to this normal infant physiology, while the modern pattern of rarely moving in and out of ketosis differs from the glucose-and-ketone cycling that would have been common across human life, and loss of that fuel switching is part of the dementia problem.
  • Reduced brain glucose use in Alzheimer's disease has been known since early PET imaging, while George Cahill's 1967 fasting work established that ketones can become a major brain fuel during starvation. [1]
  • The glucose problem begins before diagnosed Alzheimer's disease, including in genetic and sporadic forms and in otherwise healthy aging, so it cannot be explained only by neurons dying late in the disease.

The brain energy problem in Alzheimer's disease

  • Aging together with carbohydrate-heavy diets, excess sugar, sedentary living, and insulin resistance can worsen low brain glucose use while suppressing endogenous ketone production, creating what amounts to chronic starvation of the brain.
  • Plaques, tangles, amyloid, and tau are central to Alzheimer's neuropathology, but clearing plaque does not by itself restore the brain energy needed to learn, store information, and recover memories.
  • Amyloid-directed drugs and metabolic approaches can be complementary; Alzheimer's disease is unlikely to be adequately addressed unless the brain energy deficit is addressed at the same time.

What the clinical trials show

  • Trials of exogenous ketones, MCT, and ketogenic diets include unblinded and randomized studies, with some small successes and many neutral or negative outcomes; most have lasted only 8-12 weeks, while Alzheimer's changes slowly and long-term dietary adherence is difficult.
  • Elizabeth Neal's ketogenic-diet randomized controlled trial in children with epilepsy demonstrates that such a diet trial can be done in neurology, although controlling diet in children is easier than maintaining a long ketogenic intervention in older adults. [2]
  • Matthew Phillips's randomized crossover trial in Alzheimer's disease improved quality of life and daily function on a modified ketogenic diet, while specific memory and cognitive measures did not significantly improve. [3]
  • Quality of life is often not measured, and attention, follow-up, group activity, and the sense that someone is caring for the participant can themselves produce a large placebo or control-group benefit.
  • In two major multidomain prevention interventions in people at risk of Alzheimer's disease, the control-group effect was about three-quarters of the beneficial effect, consistent with exercise, cognitive training, social contact, and active care improving people's lives.
  • Functional ability, communication with family and neighbors, and a better life matter more to patients than biomarker changes.

APOE4, disease stage, and heterogeneity

  • One ketone-product study found cognitive benefit that was markedly weaker in APOE4 carriers, making genotype a plausible modifier of response.
  • The roughly 40-versus-40, six-month MCT study in mild cognitive impairment found no APOE4 effect, but only about 10-12 APOE4 carriers were in each group, so the trial was not powered to settle that question. [4]
  • APOE4 is currently more useful as a research tool than a clinical decision tool: noncarriers are not protected, homozygous carriers have higher risk, and testing can create misleading reassurance even though risk can still be mitigated.
  • Prevention should start early because the same lifestyle risks also drive hypertension, obesity, cancer, and type 2 diabetes; severe type 2 diabetes is already occurring in teenagers, even to the point of kidney transplantation.
  • Advanced Alzheimer's disease is not automatically beyond help: for most severely affected people the effort or cost may no longer be worthwhile, yet periods of lucidity and benefit are seen anecdotally, so there is no justified MMSE cutoff below which trying is automatically futile.
  • Metabolic dysfunction is a contributing factor, not a guarantee that correcting metabolism will eliminate Alzheimer's disease; genetics, other diseases, infections, falls, head trauma, and concussion can all change the response.
  • Beta-amyloid changes can be seen after concussion in university athletes in their twenties and can still leave a fingerprint decades later, illustrating how brain injuries and other exposures can accumulate alongside metabolic risk.

A multidomain lifestyle strategy

  • Exercise, cognitive activity, sleep, stress, and metabolic health all matter, so multiple components are used because no single intervention has been shown to solve every case.
  • A four-component intervention also hedges against imperfect adherence; insulin control is a major constraint, and overnight fasting, possibly around 16 hours, should allow endogenous ketone production to occur.
  • Mild cognitive impairment changes slowly, so a statistically significant shift of one or two points on a memory test may not be clinically meaningful unless it changes daily life or quality of life.

Eric Sprott's funding and the new program

  • Eric Sprott's donation creates the opportunity to combine research with public and clinician outreach; at age 81 he feels healthier on a mainly keto-carnivore diet, his partner has followed a ketogenic diet for more than 20 years, and the goal is for people and doctors to act on preventable risk.
  • Useful action does not have to wait for another five years of research: refined carbohydrate can be reduced now, and exercise is important in part because it increases brain ketone uptake.
  • Cutting carbohydrate intake by about 50% is already useful but may not raise ketones much, so MCT is added to increase ketone availability without demanding a strict ketogenic diet.
  • A small retirement-home study showed that people in their eighties could sustain a reduced-carbohydrate diet while still receiving two smaller desserts a day by lowering the overall carbohydrate load, fruit juice, and soft drinks. [5]
  • The main multidomain project combines reduced carbohydrate, MCT, exercise, and an omega-3 supplement, alongside knowledge mobilization through Keto Celebration and education designed to change health-professional practice.

Type 2 diabetes as an actionable Alzheimer's risk

  • Prevention and slowing established disease are different goals, but type 2 diabetes is one of the top three or four modifiable risk factors for Alzheimer's disease and refined sugar intake is changeable.
  • UK and North American type 2 diabetes programs, including Virta Health and David Unwin, can eliminate medications and insulin; the more precise terms are "remission" or "reversal," not "cure."
  • Preventing or reversing type 2 diabetes does not guarantee prevention of Alzheimer's disease, but reducing a major risk factor should protect the heart, kidneys, and liver and is expected to delay memory problems: "forget Alzheimer's disease" and think below the neck.
  • "Type 3 diabetes" draws attention to brain insulin resistance, but it may also steer attention toward diabetes drugs alone; reduced carbohydrate could potentially be combined with GLP-1, SGLT, or other appropriate drugs.
  • Persistent medical resistance to reducing carbohydrate and sugar intake is the same century-long problem explored by Gary Taubes in Rethinking Diabetes. [6]

SPARCUS and the broader goal

  • SPARCUS is the Sprott Prevent Alzheimer Research Collaboration at the University of Sherbrooke, built around research and getting the public to take prevention seriously.
  • Clinician education can use CME, communities of practice, practitioner exchange, and the experience of patients who have succeeded with metabolic interventions.
  • Metabolic health, mental health, and cognitive health are moving toward the same connected field, and philanthropy from people such as Eric Sprott and the Baszucki family can help change research priorities and medical practice.

References

  1. [07:18] Brain Metabolism during Fasting — https://doi.org/10.1172/JCI105650
  2. [12:27] The ketogenic diet for the treatment of childhood epilepsy: a randomised controlled trial — https://doi.org/10.1016/S1474-4422(08)70092-9
  3. [13:18] Randomized crossover trial of a modified ketogenic diet in Alzheimer’s disease — https://doi.org/10.1186/s13195-021-00783-x
  4. [16:20] A ketogenic drink improves cognition in mild cognitive impairment: Results of a 6-month RCT — https://doi.org/10.1002/alz.12206
  5. [27:55] A reduced carbohydrate diet improves glycemic regulation in hyperglycemic older people in a retirement home: the SAGE study — https://doi.org/10.1139/apnm-2024-0277
  6. [34:52] Rethinking Diabetes — https://www.penguinrandomhouse.com/books/561552/rethinking-diabetes-by-gary-taubes/
[–] jet@hackertalks.com 5 points 16 hours ago* (last edited 16 hours ago)

Do you have crypto donation options? I checked all the posted payment providers above and didn't see any

there is a post from 3 years ago with crypto donation addresses, are they still valid? https://lemmy.world/post/12531572

[–] jet@hackertalks.com 2 points 17 hours ago

A entire guide to doing keto! Written for clinicians, but anyone can read it.


Metabolic disorders represent a growing global health burden, with a high percentage of adults demonstrating some features of metabolic dysfunction. The Society of Metabolic Health Practitioners recognised the need for a consensus guideline for the implementation of therapeutic carbohydrate reduction (TCR), which is increasingly used in clinical practice. This document updates a 2019 expert panel-derived statement by incorporating new evidence and applying a formal consensus methodology. This guideline was developed using a structured Delphi consensus process with predefined agreement thresholds. The steering committee reviewed and expanded the 2019 document during an initial round (pre-Delphi, round 0), after which panel feedback informed substantial structural revision and integration of comments, resulting in a redrafted version that formed the basis for subsequent consensus rounds. Statement development was informed by a targeted, non-systematic review of human studies from research databases. Given the heterogeneous and evolving evidence base, no formal evidence grading framework was applied. After three rounds of feedback and iterations an anonymous survey was conducted. This Delphi consensus-based guideline provides practical, evidence-informed recommendations for the implementation of TCR in metabolic disorders. Consensus was achieved across key domains relating to the implementation of TCR in metabolic disorders. A whole foods TCR approach is nutritionally sufficient and may be tailored to a wide range of cultural and personal preferences, focusing on protein, healthy fats from whole foods, and vegetables. Therapeutic carbohydrate reduction is safe and effective for a range of metabolic disorders. Adaptation effects are generally mild, short-lived, and easily managed, and long-term adherence is both possible and enjoyable. Further research is required to refine application across diverse populations and clinical contexts.

Full guideline - https://doi.org/10.4102/jmh.v9i1.152

[–] jet@hackertalks.com 0 points 5 days ago (1 children)

Yup! ⏚ - when your outside touching the ground with your feet, you have a different potential... shoes in a office.... your just floating.

[–] jet@hackertalks.com 2 points 5 days ago

Bret Schur gives a overview of the paper - https://www.youtube.com/watch?v=PLdXbHBD_MM

He does call it a control trial, but i think he just got confused with RCT (the paper defines this as clinical trail), other then that, great video.

[–] jet@hackertalks.com -1 points 5 days ago (1 children)

There are several studies that proof seed oil is safe, someone linked a pair up in the thread. This person don’t want to listen to anything that says they are wrong and of course they have no proof to back their claims.

Your already insulting me, and my due diligence, why do you expect me to spend time satisfying your curiosity with links?

[–] jet@hackertalks.com 1 points 5 days ago (2 children)

What is something that everybody does right now that is common and normal

You’re making the claim that seed oils are bad. I’m expressing doubt. The burden of proof is yours.

Here is a thought experiment: processed industrial oils were not a dietary input before ww1, would you say people are healthier now? Would you say heart disease is higher or lower now then before ww1?

[–] jet@hackertalks.com 1 points 5 days ago (1 children)

Do you deny that processed industrial oils were not a major dietary input before world war 1? If they have no impact, then it wont matter if we avoid them. If they have a impact, then its important we examine the impact directly.


Gram for gram, soy protein has at least a thousand times the estrogenic activity of hormone-treated beef. So if you're worried about hormones in beef, you should be more worried about soy.

Sydney doctor Dr Paul Mason and co-host Alison work through your comments: hormone growth promotants vs soy isoflavones, soy formula, lavender and tea tree oil in young boys, BPA on receipts and "BPA-free" plastics, feminised fish downstream of sewage, whether the Chinese really stayed healthy on 80% rice and vegetables, what Denise Minger found in the raw China Study data, how Dean Ornish's "reversal" of heart disease came down to 0.01 mm on an angiogram, why half of "70% blockages" aren't 70% when a computer measures them, polar bear liver vs beef liver, vitamin A and measles, oxalate dumping, and whether protein can help hypoglycaemia.

Plus two In the News segments: the herbicide atrazine and the frogs that changed sex, and Novo Nordisk's ZEUS trial, where blocking inflammation didn't prevent heart attacks.

generated summary

Hormones in meat, soy, BPA, and environmental estrogens

  • Hormone growth promotants are legal in cattle in the US and Australia except Tasmania; ear implants slowly release hormones, increasing growth by about 10–20% while producing leaner meat. They are not approved for poultry or pigs in either country.
  • The European Union has banned growth-promoting hormones since the 1980s. Meat naturally contains hormones, and implanted beef generally contains about 2–10 times more estradiol or estrogen residue.
  • Soy is a much bigger estrogenic concern because its isoflavones mimic estrogen at receptors. Traditional soy foods provide roughly 3–4 mg of isoflavones per gram of protein, and gram for gram soy protein has at least 1,000 times, probably nearer 10,000 times, the estrogenic activity of beef produced with growth-promoting hormones.
  • In premenopausal women, 60 g of soy protein daily delayed menstruation or lengthened the follicular phase and suppressed the mid-cycle LH and FSH surges, demonstrating measurable hormonal effects from dietary soy. [1]
  • Setchell's 1997 Lancet work found that four-month-old infants fed soy formula received 6–11 times the isoflavone dose per kilogram that had produced hormonal effects in adults. [2]
  • Newborn girls normally lose maternal estrogen effects after birth, but soy-formula-fed newborn girls took longer for their uterus and vaginal lining to return to normal. [3]
  • Three prepubertal boys aged 4, 7, and 10 developed gynecomastia while using topical products containing lavender or tea tree oils; the gynecomastia receded after the products were stopped. [4]
  • BPA is a plastic building block with estrogenic activity and is detectable in the urine of most people in Western populations; thermal receipt paper is another important source.
  • Cashiers handling thermal paper had substantially higher urinary BPA, reaching up to roughly three times normal levels, and Biedermann found that receipt contact left BPA on the skin, with about 27% unwashed after two hours and wet or greasy skin increasing transfer about tenfold. [5][6]
  • "BPA-free" products can use bisphenol S, so removing BPA does not necessarily remove estrogenic bisphenol exposure.
  • Short dietary interventions that eliminated canned and plastic-packaged foods rapidly lowered urinary BPA, demonstrating that exposure can fall quickly when food-packaging sources are removed. [7]
  • Sewage works do not fully remove estrogenic compounds from contraceptives, hormone therapy, and foods. Wild roach downstream of sewage works developed widespread intersex characteristics, and later work found similar reproductive disruption in white suckers and rapid feminizing responses in male fish exposed to wastewater effluent. [8][9][10]

Atrazine and endocrine disruption

  • Atrazine remains permitted in the US and Australia despite its European ban, and a recent US analysis estimated that about 25% of continental US rivers were contaminated with atrazine at levels that could cause health concern. [11]
  • Hayes's 2002 frog work found hermaphroditism and demasculinization at low, environmentally relevant atrazine concentrations, with markedly reduced testosterone in exposed males. [12]
  • A 2010 follow-up found that about 10% of atrazine-exposed genetic males became functional females, while the remaining males had demasculinization, impaired reproductive development, and reduced fertility. [13]
  • Human observational literature has also associated atrazine exposure with impaired fetal growth and birth-defect signals, supporting reverse-osmosis filtration for drinking water.

The China Study, Ornish, angiography, and stents

  • The China Study book by T. Colin Campbell and Thomas Campbell grew out of the China-Cornell-Oxford project and uses epidemiologic associations from rural China to support avoiding animal products. [14][15]
  • The original project covered villages in 65 counties and about 100 people in each location, comparing diet and health patterns; this type of epidemiology can find correlations but cannot prove that the diet caused the health outcome. [15]
  • Denise Minger reanalyzed the raw China Study data and found that all-cancer mortality was about four times more strongly associated with plant protein than animal protein, while wheat protein had a stronger association with cardiovascular disease than animal protein. [16]
  • Dean Ornish's Lifestyle Heart Trial combined a very-low-fat vegetarian diet with exercise, smoking cessation, stress management, meditation or yoga, and group support, so the diet cannot be isolated as the cause of the result. [17]
  • The coronary angiography change was tiny: converting the percentage result to vessel diameter gives roughly 0.01 mm, while measurement error with angiography can be around 10–20 times larger.
  • Angiogram interpretation is also subjective. In a large comparison using a 70% stenosis threshold, about half of lesions visually judged at or above 70% were below 70% by quantitative coronary angiography. [18]
  • Large randomized trials in stable coronary disease have repeatedly found that coronary artery stenting does not help people live longer. [19][20]

Vitamin A, liver, and measles

  • Polar-bear liver contains vastly more vitamin A than beef liver because of biomagnification; the Inuit taboo against eating it and historical explorer poisonings illustrate that genuine hypervitaminosis A from liver is possible.
  • Beef or lamb liver is much lower in vitamin A. Chronic toxicity would generally require something on the order of 150 g of raw beef liver every day for months, not ordinary liver intake.
  • A 1986 paper documented two chronic hypervitaminosis A cases; one patient had eaten up to about 100 g of beef liver daily for 8–9 years and also used a vitamin A supplement. [21]
  • A much more extreme recent case involved a 37-year-old man eating up to 17 kg of beef liver per week and developing hypervitaminosis A liver disease. [22]
  • Excess preformed vitamin A can cause peeling skin, headache, vomiting, muscle pain, liver injury, and fetal harm in pregnancy. Carrots can turn skin orange through beta-carotene, but conversion to active vitamin A is regulated and is much less efficient than obtaining preformed vitamin A from animal foods.
  • In Barclay, Foster, and Sommer's measles trial, 180 children were randomized; 6 of 88 receiving two 200,000-IU vitamin A doses died versus 12 of 92 controls. [23]
  • Hussey and Klein then studied 189 children with severe measles in South Africa; 2 deaths occurred in the vitamin A group versus 10 in the control group after a total 400,000 IU dose. [24]

Oxalates and "oxalate dumping"

  • Sally K. Norton's "oxalate dumping" theory says long-term high-oxalate foods create tissue stores that are released after those foods are removed, producing rashes, grainy stools, burning urine, depression, and joint pain; the hypothesis is unpersuasive because it is set up to dismiss normal blood or urine oxalate measurements.
  • Blood and urine oxalate measurements can detect genuine excess. Kidney failure causes tissue accumulation, and after a functioning kidney transplant urinary oxalate is initially high and then falls rapidly as retained oxalate is cleared. [25]
  • In people tested specifically for suspected "oxalate dumping," urinary oxalate was not detected in any case.
  • Vague symptoms attributed to dumping deserve symptom-specific investigation. Standard urine testing detects only about one-third of known uropathogens, so a negative routine culture does not exclude every urinary pathogen. [26]
  • Poor concentration or fatigue warrants evaluation for issues such as B12 or iron deficiency, inflammation, infection, and other causes appropriate to the symptom, without assuming dumping.
  • Oxalate itself can cause genuine disease: calcium oxalate is a common kidney-stone component, genetic hyperoxaluria can increase hepatic oxalate production, and severe oxalate excess can deposit in tissues and joints.
  • The old advice to manage oxalate stones simply by drinking more water while continuing high-oxalate foods makes little sense.
  • Fat malabsorption is an important mechanism in genuine oxalate pathology: unabsorbed fat binds calcium, leaving less calcium to bind oxalate, and intestinal oxalate absorption can rise from roughly 5–10% to above 30%; fecal fat testing can help identify the problem. [27]

ZEUS, inflammation, infection, and atherosclerosis

  • Novo Nordisk's ZEUS trial used a monoclonal antibody to suppress the IL-6 pathway and lower CRP, testing the idea that reducing inflammation would reduce cardiovascular events. [28]
  • The trial lowered inflammatory signaling but did not reduce heart attacks, strokes, or cardiovascular death; serious infections were more frequent, and only company topline results were available at the time of the episode. [28]
  • Association is not causation. Inflammation in coronary disease can be part of the immune response to infection, so suppressing that response does not necessarily remove the underlying cause.
  • In a 2006 paper, Ott and colleagues recovered 38 atherosclerotic plaque specimens with a cutting catheter and found bacterial DNA in all 38, while control vessels had none. [29]
  • Coronary artery disease and atherosclerosis are infectious diseases, with inflammation acting like a firefighter at the scene rather than the fire itself.
  • Corticosteroids can suppress inflammation and reduce symptoms while increasing susceptibility to infections and cancers, illustrating the difference between suppressing an immune response and removing what triggered it.
  • Chronic infections, including fungal infections, can provoke immune cross-reactivity against similar host tissues and may contribute causally to autoimmune disease.

Hypoglycemia, protein, and ketones

  • Hypoglycemia can be dangerous, especially for people using insulin, so insulin-managed diabetes requires medical supervision rather than casual dietary experimentation.
  • On a theoretical dietary basis, protein can support glucose through gluconeogenesis. In a 2023 pilot, subjects exercised in the afternoon and 50 g of whey protein roughly doubled glucagon and raised average glucose from 5.9 to 7.8 mmol/L versus water. [30]
  • Protein has a longer glucose effect than carbohydrate because gluconeogenesis unfolds over hours, so protein before bed could theoretically smooth a later nocturnal low without producing only a short glucose spike.
  • Tracer work found that about one-fifth of ingested protein carbon can enter circulating glucose over the following hours. [31]
  • The usual Australian biochemical cutoff is below 3.5 mmol/L, but keto-adapted people can have lower glucose without hypoglycemic symptoms because the brain can use ketones; symptoms such as sweating, tremor, nausea, and intense hunger matter clinically.
  • Longstanding poorly controlled diabetes can blunt awareness of low glucose, and beta-blockers can also mask warning symptoms, so low readings in those settings need more caution.
  • George Cahill's fasting work is recalled as showing people fasted for weeks, entered starvation ketosis, then received insulin and remained clinically well even as glucose approached about 1 mmol/L; the accompanying ketone fall was taken as evidence that the brain was relying heavily on ketones.
  • The brain is only about 2% of body mass but uses roughly 20% of total energy, making it especially vulnerable to metabolic dysfunction; dementia is increasingly called "type 3 diabetes," which is a topic for another episode.

References

  1. [04:10] Biological effects of a diet of soy protein rich in isoflavones on the menstrual cycle of premenopausal women — https://doi.org/10.1093/ajcn/60.3.333
  2. [05:16] Exposure of infants to phyto-oestrogens from soy-based infant formula — https://doi.org/10.1016/S0140-6736(96)09480-9
  3. [06:31] A Longitudinal Study of Estrogen-Responsive Tissues and Hormone Concentrations in Infants Fed Soy Formula — https://doi.org/10.1210/jc.2017-02249
  4. [07:01] Prepubertal Gynecomastia Linked to Lavender and Tea Tree Oils — https://doi.org/10.1056/NEJMoa064725
  5. [09:38] Occupational exposure of cashiers to Bisphenol A via thermal paper: urinary biomonitoring study — https://doi.org/10.1007/s00420-016-1132-8
  6. [09:55] Transfer of bisphenol A from thermal printer paper to the skin — https://doi.org/10.1007/s00216-010-3936-9
  7. [11:31] Food packaging and bisphenol A and bis(2-ethyhexyl) phthalate exposure: findings from a dietary intervention — https://doi.org/10.1289/ehp.1003170
  8. [12:54] Widespread Sexual Disruption in Wild Fish — https://doi.org/10.1021/es9710870
  9. [13:28] Reproductive disruption in fish downstream from an estrogenic wastewater effluent — https://doi.org/10.1021/es0720661
  10. [13:34] Demasculinization of male fish by wastewater treatment plant effluent — https://doi.org/10.1016/j.aquatox.2011.02.007
  11. [14:02] Pernicious Pesticide: Atrazine's Growing Threats to Drinking Water, Rivers, People, and Wildlife — https://www.biologicaldiversity.org/campaigns/pesticides_reduction/atrazine/Pernicious-Pesticide-report.html
  12. [14:21] Hermaphroditic, demasculinized frogs after exposure to the herbicide atrazine at low ecologically relevant doses — https://doi.org/10.1073/pnas.082121499
  13. [14:52] Atrazine induces complete feminization and chemical castration in male African clawed frogs (Xenopus laevis) — https://doi.org/10.1073/pnas.0909519107
  14. [16:08] The China Study — https://www.benbellavegan.com/book/the-china-study/
  15. [16:26] Diet, lifestyle, and the etiology of coronary artery disease: the Cornell China Study — https://doi.org/10.1016/S0002-9149(98)00718-8
  16. [18:21] The China Study: A Formal Analysis and Response — https://deniseminger.com/2010/08/03/the-china-study-a-formal-analysis-and-response/
  17. [20:02] Can lifestyle changes reverse coronary heart disease? The Lifestyle Heart Trial — https://doi.org/10.1016/0140-6736(90)91656-U
  18. [24:12] Comparison of Physician Visual Assessment With Quantitative Coronary Angiography in Assessment of Stenosis Severity in China — https://doi.org/10.1001/jamainternmed.2017.7821
  19. [25:12] Optimal Medical Therapy with or without PCI for Stable Coronary Disease — https://doi.org/10.1056/NEJMoa070829
  20. [25:12] Initial Invasive or Conservative Strategy for Stable Coronary Disease — https://doi.org/10.1056/NEJMoa1915922
  21. [28:47] Hepatic and dermatologic manifestations of chronic hypervitaminosis A in adults. Report of two cases — https://doi.org/10.1016/0002-9343(86)90726-6
  22. [29:20] Histological Findings of Hypervitaminosis A Liver Disease — https://doi.org/10.1016/j.gastha.2024.08.010
  23. [31:23] Vitamin A supplements and mortality related to measles: a randomised clinical trial — https://doi.org/10.1136/bmj.294.6567.294
  24. [31:41] A Randomized, Controlled Trial of Vitamin A in Children with Severe Measles — https://doi.org/10.1056/NEJM199007193230304
  25. [34:18] Effect of renal transplantation on serum oxalate and urinary oxalate excretion — https://doi.org/10.1159/000188014
  26. [35:35] The Clinical Urine Culture: Enhanced Techniques Improve Detection of Clinically Relevant Microorganisms — https://doi.org/10.1128/JCM.00044-16
  27. [38:23] Pathophysiology and Treatment of Enteric Hyperoxaluria — https://doi.org/10.2215/CJN.08000520
  28. [39:39] Novo Nordisk provides update on the ZEUS phase 3 trial in people with ASCVD, CKD and inflammation — https://www.novonordisk.com/news-and-media/news-and-ir-materials/news-details.html?id=916587
  29. [43:08] Detection of diverse bacterial signatures in atherosclerotic lesions of patients with coronary heart disease — https://doi.org/10.1161/CIRCULATIONAHA.105.579979
  30. [48:18] Protein Ingestion in Reducing the Risk of Late-Onset Post-Exercise Hypoglycemia: A Pilot Study in Adolescents and Youth with Type 1 Diabetes — https://doi.org/10.3390/nu15030543
  31. [49:39] Glucose appearance rate following protein ingestion in normal subjects — https://doi.org/10.1080/07315724.1992.10718270
[–] jet@hackertalks.com -1 points 5 days ago (6 children)

Okay, so what is the mechanism and the damage that seed oils or industrial process do?

The plant sterols are similar to, but don't function the same as, human cholesterol, so it interferes with human hormonal function (this is why LDL lowers). Industrial leftover chemicals, such as the solvents, are a likely source of contamination at low doses, but we don't know the effect over time. Quite frankly demanding proof that the new food isn't safe is backwards, you should be demanding proof that it is safe, and demand to read the human studies (animal studies too) looking at all cause mortality.

[–] jet@hackertalks.com -2 points 5 days ago* (last edited 5 days ago) (8 children)

humans have existed for about 2.5M years, Canola oil for about 100 years. A new food to the human organism is going to have health effects, the premise of this post is what are people doing now that will surprise them as unhealthy.... industrial processed oils as a primary dietary fat source is a great example... everyone assumes they are healthy and natural.

The seed oil itself is a new food to the human experience, not just how its processed, but its a double whammy packaged together. You can get most people to agree that highly processed foods are bad for health, but most silently carve out an exception for the industrial processed oils.

Because animal fats in general seem to be worse for your heart health than plant fats(or they increase your LDL), should we then focus on using red palm oil/olive oil.

Agreed that plant fats, and industrial processed oils lower LDL - however, is that actually healthy? LDL is not a disease, you would die without it, you need your lipoproteins to function. The vilification of LDL for the damage sugar (highly processed or not) has done is quite the misstep in public health in the last 50 years.

[–] jet@hackertalks.com -2 points 5 days ago* (last edited 5 days ago) (11 children)

Canola oil didn't exist during the American Revolution - it's a highly processed industrial oil pretending to be food - eggs in butter isn't unhealthy at all.

canola oil - how its madehttps://www.canolacouncil.org/about-canola/processing/

[–] jet@hackertalks.com 0 points 5 days ago

What is something that everybody does right now that is common and normal but is actually probably very unhealthy?

Because we’ve always done it makes it okay?

okay != healthy, you have moved the conversation from health outcomes to your personal moral context.

[–] jet@hackertalks.com 2 points 5 days ago

sugar (fructose, glucose), neuro-stimulants, cardiovascular stressors, inflammation.


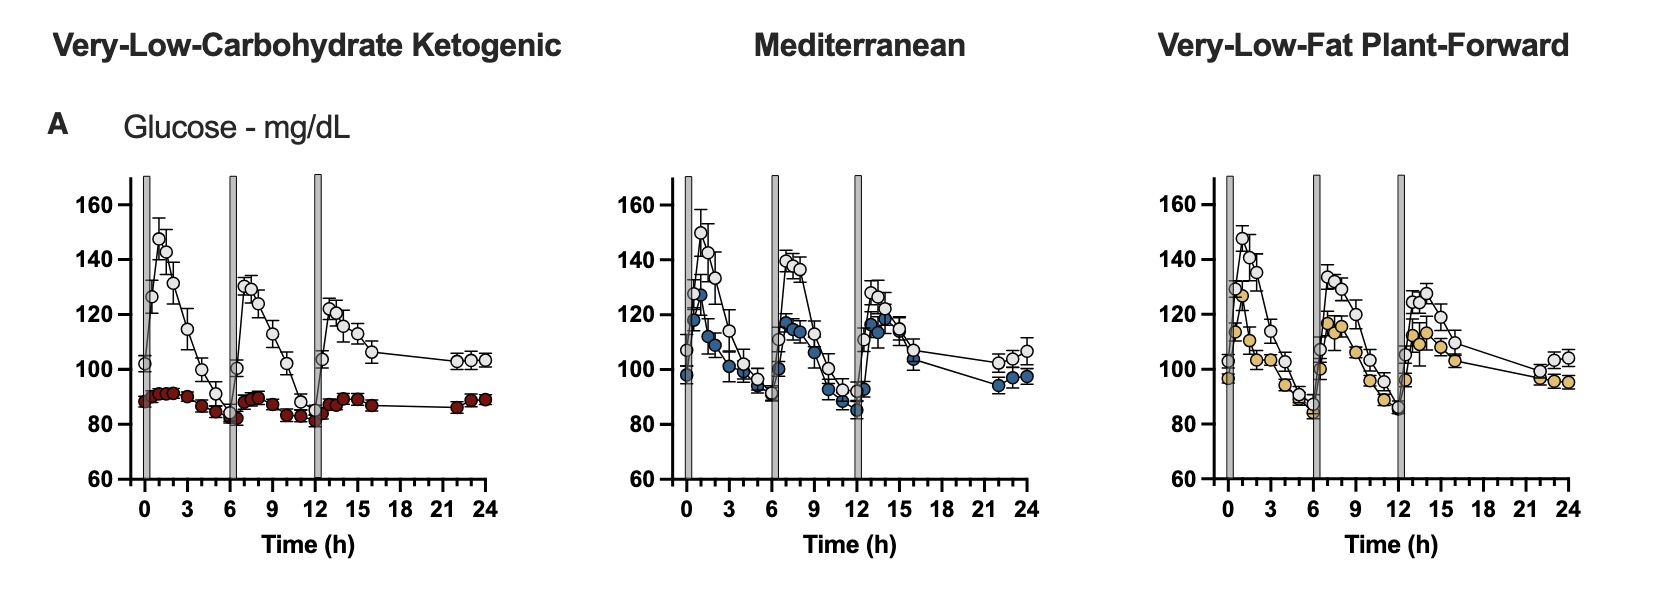
The influence of diet macronutrient content on the cardiometabolic effects of weight loss in people with metabolically unhealthy obesity (prediabetes and hepatic steatosis) has important clinical implications. We evaluated the cardiometabolic effects of moderate (∼10%) weight loss induced by three popular diets with markedly different macronutrient composition (very-low-carbohydrate ketogenic, Mediterranean, and very-low-fat plant-forward). Weight loss increased muscle insulin sensitivity by ∼50% in all groups but caused a two-to-three-fold greater increase in hepatic insulin sensitivity in the very-low-carbohydrate group than the other groups (p < 0.001). Intrahepatic triglyceride content, hepatic de novo lipogenesis, glycated hemoglobin, and 24-h serial plasma glucose and insulin decreased most in the very-low-carbohydrate group. There were no differences among groups in LDL-cholesterol, apolipoprotein B, or 24-h plasma triglyceride concentrations. These results demonstrate that a very-low-carbohydrate diet has greater cardiometabolic benefits, particularly in hepatic metabolic function, than matched 10% weight loss induced by a Mediterranean or very-low-fat diet in people with metabolically unhealthy obesity. This study was registered at ClinicalTrials.gov (NCT02706262).

Full Paper - https://doi.org/10.1016/j.cmet.2026.07.020


I've had a few friends kick off keto/carnivore and the question keeps coming up - what should they measure before they start, 3m, 6m etc?


Crispy pan fried salmon (ghee), crispy bacon with some garlic, chili, and onion... the bacon fat used to cook the sunny side up duck eggs.... finger licking good!

With pork bone broth for desert.


By 2020, being vegan was cool. A few years later, it faltered. So what happened? I sit down with nutrition scientist Simon Hill to unpack the truth about plant-based meat, protein and supplements, and how eating plants got tangled up with masculinity and politics.

generated summary

Why the plant-based movement collapsed

  • By 2020 plant-based eating had become mainstream, but the cultural mood shifted sharply afterward. The nutrition science did not reverse; public enthusiasm moved toward animal-based and carnivore diets.
  • Beyond Meat became a symbol of the reversal. Plant-based meat products remained far more expensive than chicken, did not reach taste parity, and were caught in a wider backlash against ultra-processed foods.
  • The failure of a company such as Beyond Meat does not mean that eating more plants failed. Whole and minimally processed plant foods remain the basis of the health case for plant-predominant eating.
  • Three forces drove the downturn: weak health messaging and lost trust, alienating behavior inside vegan advocacy, and post-2020 cultural and political changes.

Health messaging and lost trust

  • Highly processed vegan burgers, nuggets, desserts, cheeses, and similar foods were sold as health foods. They can help people transition away from animal foods, but they are not the foods behind the strongest long-term health evidence.
  • There are three routes into plant-based eating: animal ethics, environmental sustainability, and human health. The ethical and environmental cases are stronger grounds for complete animal-food exclusion than human health alone.
  • Mediterranean, MIND, DASH, vegetarian, and vegan diets can all produce good health outcomes when they center on minimally processed foods. The evidence does not establish that a fully plant-exclusive diet is significantly healthier than every other well-constructed pattern.
  • Past advocacy often oversimplified concerns about vitamin B12, protein, fat intake, and individual variability. A diet that works extremely well for one person does not necessarily work identically for everyone.
  • Rich extrapolated too much from his own success and previously platformed advocates whose health message was carrying an ethical goal; Simon sometimes tiptoed around irresponsible education on protein, B12, and very-low-fat plant-based diets.
  • A fully plant-exclusive diet may not work for absolutely everyone. People should not be made guilty or ashamed if they feel better and remain healthier on a plant-predominant diet.
  • Personal success can become evangelism: someone feels dramatically better, assumes others will too, and then blames people who have a different experience for doing the diet incorrectly. The same pattern occurs in carnivore and ketogenic communities.
  • Across the broader evidence base, the people doing well over decades tend to eat high-fiber, plant-predominant diets that are lower in saturated fat and ultra-processed foods.
  • Trust erodes when animal-rights ethics are hidden inside a health message. Health information should be given transparently even when the strongest motivation for avoiding animal foods is ethical.
  • Absolute messages such as all dairy being unhealthy, all animal protein being harmful, or fish being bad for health do not fit the nutrition science. Fermented dairy such as yogurt and cheese can be neutral or beneficial depending on context, and fatty fish is generally neutral or beneficial.
  • Social media rewards certainty, simplicity, and confidence, while good science contains uncertainty and context. This created incentives for stronger and simpler vegan health messages than the evidence could support.
  • A practical nutrition philosophy is simple without being absolute: eat a plant-predominant pattern built from minimally processed foods, keep ultra-processed packaged foods limited, and choose the carbohydrate level that leaves you feeling best.

Protein and micronutrients

  • The old message that everything takes care of itself on a vegan diet except perhaps B12 was too simple. Removing fish, meat, and other animal foods changes protein and micronutrient intake depending on what foods take their place.
  • Protein-rich plant foods such as tofu, tempeh, edamame, chickpeas, beans, and lentils are better swaps for animal protein than simply eating more fruit and vegetables.
  • Plant-exclusive diets need attention to vitamin B12, omega-3 fats, iodine, zinc, and overall protein. For a busy person who is not carefully tracking food, a multivitamin can function as nutritional insurance, with omega-3 supplementation added separately.
  • Protein matters, but sarcopenia in the general population is driven more by inactivity than by inadequate protein. Resistance training supplies the missing stimulus for maintaining and building muscle, while the average person already consumes enough protein.

Why vegan advocacy pushes people away

  • Moral superiority, scolding, shame, and purity tests make the movement less attractive. People generally do not want to join a community that begins by telling them they are bad or morally deficient.
  • Ardent animal-rights activism has a role in sounding an alarm and defining moral boundaries, but alarm-raising and mass persuasion are different jobs.
  • For broad persuasion, attraction works better than promotion: live the ethic in a way that looks healthy, functional, and appealing, then help people who become curious without demanding immediate ideological purity.
  • Strong ethical conviction and welcoming communication can coexist. Compassion for animals can also be directed toward people who disagree, and internal attacks over who is vegan enough weaken the movement.
  • Getting 80% of people to do Meatless Mondays can accomplish more for animal welfare than getting 1% of people to become 100% vegan; purity tests can destroy useful opportunities for partial change.

The post-2020 cultural shift

  • Veganism became associated with "wokeness," institutional control, and the political left, while meat became tied to red-pill identity, freedom, and masculinity. "Soy boy" became an insult used to make plant-based eating look incompatible with manhood.
  • Meat historically signaled hunting ability, physical strength, and provision for a group; modern meat usually signals shopping. What is on a plate no longer demonstrates those capacities.
  • Young men looking for status, dating success, and a stronger identity can be drawn toward external signals such as heavy lifting, steak, and rejection of soy. Physical fitness matters, but long-term partnership also depends heavily on emotional capacity, listening, and not becoming defensive or reactive.
  • Security and self-worth come from narrowing the gap between the person you want to be and the way you actually behave: being trustworthy, loyal, dependable, accountable, and able to live in line with your values.
  • Food choice does not determine male identity. Equating meat with masculinity also benefits large meat companies, even though the same message is often packaged as resistance to institutional manipulation and support for local food sovereignty.
  • Protecting vulnerable beings, reducing environmental harm, and making difficult choices in line with personal ethics can be expressions of strength, not weakness.

Where to go from here

  • The goal does not need to be perfect veganism. A stronger direction is to eat as plant-exclusive as is compatible with feeling healthy, nourished, and physically capable while also weighing animal welfare and environmental impact.
  • To start, reduce red meat, white meat, and processed meat and add more tofu, tempeh, lentils, beans, chickpeas, fruits, vegetables, whole grains, nuts, and seeds.
  • Do not remove animal protein without planning the protein source that takes its place. Aim for at least 1.2 g/kg of protein, rising to about 1.6 g/kg when very physically active; a protein shake can add roughly 40 g.
  • A simple starting supplement plan is a multivitamin plus DHA/EPA omega-3 from fish oil or algae oil, with later refinement based on the individual diet.

References None.


I ate more than 100 pounds of meat in 30 days while following the Lion Diet: no dairy, eggs, seafood, coffee, supplements, or plant foods—just ruminant meat, salt, and water. In this video, I break down what actually happened to my digestion, bloodwork, omega-3 levels, cholesterol, and overall health, while separating the carnivore diet’s legitimate strengths from the hype.

We also dive into the science of carnivore diets, fiber, IBS, inflammatory bowel disease, microbiome diversity, vitamin C, calcium, omega-3s, ketosis, autoimmune disease, and mental health. The goal here isn’t to convince you to become carnivore. It’s to ask a better question: Is carnivore a diet everyone should follow, or a therapeutic tool that may be unusually useful for the right person at the right time?

generated summary

Why I tried carnivore again

  • The carnivore diet rose rapidly as advocates promoted it for athletic performance, body composition, obesity, autoimmune disease, mood disorders, fatigue, skin problems, and other chronic illnesses; more recently, major advocates such as Paul Saladino moved away from strict carnivore and reintroduced fruit and other plant foods.
  • Carnivore did not simply fail as a fad: beneath the internet debates and social-media hot takes is a more nuanced story, which motivated another trial.
  • An earlier fairly liberal five-month carnivore diet included dairy, eggs, and coffee and was a surprisingly positive experience; the later 30-day trial used the lion diet, the strictest and most extreme version, with no dairy, eggs, seafood, coffee, or organ meats—just meat, salt, and water.
  • The experience is one data point and a springboard into the bigger story of carnivore's popularity, controversies, what the science shows, and what remains to be learned.

Gut health

  • Zero fiber did not cause constipation: bowel movements occurred every day, and by day 30 they were about as close to perfect as they had ever been.
  • A 2012 World Journal of Gastroenterology study found that eliminating dietary fiber in people with irritable bowel syndrome with constipation improved bowel frequency from one movement every 3.75 days to one per day, eliminated bloating and straining, and produced worse symptoms as fiber intake increased. [1]
  • Ulcerative colitis took several years of life away, showing how severe inflammatory bowel disease can be.
  • A case series of 10 medically confirmed Crohn's disease or ulcerative colitis patients included severe cases requiring biologic drugs or intestinal surgery; most had already tried vegan, vegetarian, low-FODMAP, paleo, and other elimination diets, and every patient experienced substantial, life-changing improvement on a fiber-free carnivore diet. [2]
  • One patient said a keto-carnivore diet let him forget he had Crohn's disease without drugs or surgery, and another said this lifestyle had allowed six years without having to worry about colitis. [2]
  • Removing carbohydrates produces ketone bodies, including in the gut, where they act as signaling molecules that can reprogram immune cells to make them less inflammatory. [3]
  • Ketone signaling may also help intestinal stem cells renew and better heal the gut lining. [4]
  • Cell Host & Microbe research found that a fiber-free diet altered the metabolism and location of the pathobiont Mucispirillum and ameliorated colitis in an animal model; at a high level, removing fiber can starve problematic gut organisms, although the actual mechanism involves intraluminal migration. [5]
  • Fiber-free diets are already used for refractory inflammatory bowel disease and can produce response rates around 60-85%; conventional medicine generally administers them as unpalatable fiber-free liquid formulas, while eating meat could achieve the same endpoint of fiber elimination.
  • A study compared 10 healthy people eating carnivore for an average of about three years with 874 matched controls eating a mixed diet with more fiber and found no significant difference in microbiome diversity metrics, challenging the assumption that dietary fiber is essential for maintaining microbiota diversity. [6]
  • Carnivore does not stop bowel movements, does not necessarily destroy microbiome diversity, and has therapeutic potential for certain people with compromised gut health, including the kind involved here; this does not make carnivore a panacea, but it makes it interesting and somewhere to start.

Nutrient deficiencies

  • Some concerns about nutrient deficiencies are legitimate and warrant serious attention, beginning with calcium: standard carnivore with dairy is not a calcium problem, but dairy-free lion diets deserve attention and concern.
  • Muscle meat provides only about 10-20 mg of calcium per 100 g versus a general target of 1,000-1,200 mg per day, requiring roughly 11 lb of beef; for years of carnivore, especially a lion diet, a calcium source such as an actual supplement, 100 g of Parmesan per day, or eggshell-derived calcium would be something to seriously consider.
  • Omega-3 is another real concern and was already a priority: a prior month of 1,000 sardines produced an omega-3 index around 16%.
  • After 30 days on nothing but ruminant meat, with no fish, sardines, or omega-3 supplements, the omega-3 index fell from 15.68% to 10.51%; 10.51% remained within the optimal range, but the decline was rapid and was expected to continue.
  • With two copies of APOE4 and vulnerability to Alzheimer's disease, maintaining high omega-3 intake is non-negotiable; a serving of grass-fed beef may provide about 50 mg of omega-3 versus roughly 1,500 mg in a can of sardines, a 30-fold difference, so in this domain sardines beat steak.
  • A subtle omega-3 deficiency is difficult to detect and could matter over decades for brain health, so any future carnivore diet would include a healthy amount of seafood or added omega-3.
  • Meat is relatively low in vitamin C, particularly after cooking, yet historical all-meat diets did not inevitably cause scurvy; in 1928 Vilhjalmur Stefansson ate nothing but meat for an entire year under continuous medical supervision at Bellevue Hospital without developing scurvy, and his physicians published the results. [7]
  • Stefansson learned this dietary pattern from Inuit populations consuming diets almost entirely composed of animal foods such as seal, whale, and caribou with minimal plant matter, without developing scurvy.
  • Vitamin C and glucose are structurally similar molecules and compete for some of the same cellular transporters; when carbohydrate and sugar intake are high, glucose floods those transporters and outcompetes vitamin C for entry into cells. [8]
  • Without sugar in the diet, vitamin C dietary needs drop because vitamin C is absorbed more efficiently.
  • Vitamin C can also be regenerated after oxidation through an NADPH-dependent antioxidant system, and a zero-carbohydrate diet that produces ketones might support that NADPH system and help regenerate vitamin C.
  • After more than 100 lb of meat in 30 days, the result was remarkably unremarkable: bowel function continued, scurvy did not occur, cheese and coffee were greatly missed, physical well-being was good, nutrient blood tests were normal, thyroid and cortisol were normal, and cholesterol was essentially unchanged; a roughly 20 mg/dL cholesterol drop was within normal noise.

Potential medical uses

  • Nothing horrific or miraculous occurred because a ketogenic diet already worked for ulcerative colitis; carnivore may be not merely a diet but a potential medical intervention for people in need.
  • Carnivore functions at its core as one of the most extreme elimination diets possible, removing almost every potential dietary trigger at once, and this can be transformative for people whose immune systems react to specific plant compounds.
  • Strong human evidence for autoimmune and inflammatory diseases beyond inflammatory bowel disease is desperately limited, but this is a deficiency in the scientific literature that needs investigation, not something to hide from or brush under the rug.
  • Unless hordes of people are simultaneously fabricating improvements in lupus, rheumatoid arthritis, multiple sclerosis, psoriasis, and other autoimmune conditions, carnivore is helping at least some people; whether it is called a fad, fringe, or salvation, the questions are why it is helping and how to avoid throwing that signal away.
  • The combination of mechanistic ketone data, microbiome research, and clinical evidence on fiber-free diets in inflammatory bowel disease is enough of a signal to warrant serious investigation.
  • Carnivore-style animal-based ketogenic diets have emerging interest for anorexia because mental health disorders are not purely abstract psychological phenomena but arise from altered neurochemistry and changes in brain metabolism; fundamentally altering brain metabolism with ketones could also improve mental health across depression, anxiety, binge eating disorder, addiction, bipolar disorder, and anorexia.
  • Patients with anorexia have said that a carnivore diet quite literally saved their lives. [9]
  • A paper on animal-based ketogenic diets in severe anorexia includes an illustrative patient, Katherine, who was 39 when interviewed, had struggled with body image since age seven, and at age 34 maintained a BMI of 10.7—on death's doorstep—and on some days subsisted on little more than lettuce with zero-calorie stevia sweetener. [9]
  • After adopting carnivore in desperation, Katherine said, "This solved all of my issues. All of them." For the first time in decades she experienced mental clarity and calm, her weight recovered to a healthy level, as did her relationships, and she remained healthy for years. [9]
  • People with mental health disorders or eating disorders should not self-manage with carnivore; eating disorders are serious, complex conditions that require professional support.
  • This belongs on clinicians' radar as a potential tool in their toolkit.
  • For anorexia, where outcomes are horrible, mortality is high, and current care is pitifully unsuccessful, curiosity about outside-the-box tools that are helping people and saving lives is necessary; this is the most reasonable thing in the world. [9]

Who should try it?

  • This is guidance rather than a prescription: carnivore makes the most sense as a therapeutic intervention for people with refractory gastrointestinal conditions, autoimmune conditions, or metabolic health conditions, and less sense for healthy people already thriving on their current diet or anyone unwilling to monitor key biomarkers.
  • Stopping carnivore reflects lack of need, not failure; different bodies need different things, and that should not be stigmatized.
  • Someone can regain health through a 30-day carnivore elimination reset or a five-year extreme lion diet and later gradually broaden the diet a little without that meaning the diet failed; the person has evolved.
  • Carnivore is not a religion or simply a movement to join or reject, but a fascinating, powerful tool that will not be right for everybody and may be exactly what someone needs at a particular moment to save their life; that deserves curiosity, not ridicule.

References

  1. [03:44] Stopping or reducing dietary fiber intake reduces constipation and its associated symptoms — https://doi.org/10.3748/wjg.v18.i33.4593
  2. [04:41] Case report: Carnivore–ketogenic diet for the treatment of inflammatory bowel disease: a case series of 10 patients — https://doi.org/10.3389/fnut.2024.1467475
  3. [06:10] Ketone body β-hydroxybutyrate ameliorates colitis by promoting M2 macrophage polarization through the STAT6-dependent signaling pathway — https://doi.org/10.1186/s12916-022-02352-x
  4. [06:17] Ketone Body Signaling Mediates Intestinal Stem Cell Homeostasis and Adaptation to Diet — https://doi.org/10.1016/j.cell.2019.07.048
  5. [06:24] Fiber-deficient diet inhibits colitis through the regulation of the niche and metabolism of a gut pathobiont — https://doi.org/10.1016/j.chom.2023.10.016
  6. [08:23] Long-term adherence to the carnivore diet and its impact on the gut microbiota: a cross-sectional study — https://doi.org/10.1530/MAH-25-0015
  7. [12:25] Clinical Calorimetry: XLV. Prolonged Meat Diets with a Study of Kidney Function and Ketosis — https://doi.org/10.1016/S0021-9258(18)76842-7
  8. [13:01] Human erythrocytes transport dehydroascorbic acid and sugars using the same transporter complex — https://doi.org/10.1152/ajpcell.00044.2014
  9. [16:58] Animal-based ketogenic diet puts severe anorexia nervosa into multi-year remission: A case series — https://doi.org/10.4102/jir.v6i1.84


Dr. Jason Fung takes a closer look at LDL cholesterol, heart disease risk, statins, and the evidence surrounding cholesterol treatment. The discussion examines whether LDL cholesterol deserves as much attention as it currently receives compared with other major cardiovascular risk factors such as diabetes, smoking, and high blood pressure. The video explores the 2026 American Heart Association cholesterol guidelines, LDL targets, statin use, cardiovascular risk, and findings discussed from several major studies.

generated summary

Guidelines and medication scale

  • As a risk factor for heart disease, cholesterol has much less importance; the key question is not whether high LDL is a risk factor, but how important that risk is.
  • The 2026 American Heart Association lipid guidelines call for screening children at ages 9–11, screening every five years by age 20, LDL targets around 55–70 mg/dL, and aggressive drug therapy when LDL is high without waiting and watching, while the evidence points the other way. [1]
  • Applying the new guidelines would medicate about 56.5% of adults aged 30–79, about 85% at ages 60–69, about 93% by age 70, and add more than 21 million people to cholesterol medication. [2]
  • That scale gives cholesterol a dominant role even though several other cardiovascular risks are much larger.

PREVENT and risk magnitude

  • The AHA PREVENT calculator was built from more than 6 million patients in 45 studies and compares diabetes, high blood pressure, smoking, kidney disease, lipids, and other cardiovascular risk factors. [3]
  • PREVENT uses non-HDL: triglycerides and HDL are separate from LDL, high carbohydrate intake raises triglycerides and lowers HDL, and non-HDL brings triglyceride-related risk into the measure even though statins and similar drugs mainly target LDL. [3]
  • A hazard ratio of 1.0 is neutral and 2.0 means double the risk, so the magnitude of a risk factor is the relevant distinction.
  • In PREVENT, diabetes raises cardiovascular risk about 60–65%, smoking about 60%, high blood pressure about 36%, kidney disease is important, and higher HDL is protective; non-HDL has a hazard ratio of 1.0 in women and only about a 5% increase in men. [3]
  • Smoking or diabetes is roughly 10–12 times more important than LDL cholesterol; because the 5% figure comes from non-HDL, which also includes triglycerides, LDL itself has even less importance.
  • A focus on medicating more than 90% of older Americans for LDL gives less attention to diabetes, smoking, and blood pressure, which carry much larger risks.

Statin use and the Women's Health Study

  • A BMJ study of national statin use shows North America using far more statins than other regions and increasing faster; in 2020 about 26.1% of the population used a statin compared with 20% or less elsewhere. [4]
  • Greater focus on diabetes and diet, including cutting carbohydrates to lower blood sugar, addresses larger risks, while doctors spend almost no time on diet and extensive time on cholesterol.
  • The U.S. uses far more statins than Japan, yet Japan has very high life expectancy and very low heart-disease rates; cholesterol does not explain the whole difference, but statins are not that important.
  • In the Women's Health Study analysis in JAMA Cardiology, women under 55 with diabetes had a hazard ratio of about 10.7 for heart disease, compared with 1.38 for LDL cholesterol; the LDL increase is still meaningful, but diabetes and metabolic syndrome carry much larger risks. [5]
  • Diet and diabetes warrant about ten times more attention than cholesterol; diet takes clinical time, more patients generate more payment, and writing a statin prescription takes seconds.

Large global cohorts

  • A New England Journal of Medicine analysis included about 1.5 million people from 34 countries and 112 studies, with an average age of 54.4 years and average follow-up of 7.4 years, and estimated the effect of modifying five major risk factors. [6]
  • Eliminating diabetes or stopping smoking substantially lowers cardiovascular risk and total mortality, while lowering cholesterol has a much smaller cardiovascular effect and no effect on total mortality; statin-mediated cholesterol lowering therefore does not change the risk of dying in these data. [6]
  • Heart disease may decrease, but if total mortality does not fall, other non-cardiac deaths must increase enough to offset the difference; total mortality is the crucial outcome. [6]
  • A 2025 New England Journal of Medicine analysis of about 2 million people from 133 cohorts estimates that not smoking adds about 4.8–5.5 cardiovascular-disease-free years and not having diabetes adds about 4.2–4.7, while low cholesterol after medication is associated with losing about 0.4–1.3 years. [7]
  • For all-cause survival, not having diabetes adds about 5.8–6.5 years, while low cholesterol after medication is associated with losing about 0.9–1.3 years; around ages 55–60, modifying hyperlipidemia adds only about 0–0.1 cardiovascular-disease-free years and loses about 0.2–0.3 years of overall life. [7]
  • Cholesterol can still be lowered in some situations, but high blood pressure, diabetes, and smoking are much more important areas of focus.

Low LDL, mortality, and dialysis

  • Sufficiently low cholesterol does not make heart disease impossible merely because plaque contains cholesterol and babies have low cholesterol; adults should not be compared with babies.
  • In the Danish study, the LDL level associated with the lowest all-cause mortality was about 140 mg/dL, LDL below about 55 mg/dL was associated with roughly 50% higher mortality, and the lowest mortality clustered around the 60th–95th percentile and not at low LDL. [8]
  • As LDL approaches very low levels, mortality rises; some very low LDL occurs with malnutrition and other illness, so very low LDL does not make heart disease impossible.
  • Dialysis patients often have LDL around 68–81 mg/dL while still having extensive heart disease.
  • Their estimated heart-disease risk is roughly 10–20 times higher than in the general population, so very low LDL does not eliminate cardiovascular disease.
  • Dialysis patients still receive cholesterol-lowering medication despite those very low LDL levels and very high cardiovascular risk.

Stopping statins and priorities

  • In a recent Lancet Healthy Longevity unblinded randomized trial of adults aged 75 years or older, stopping statins was compared with continuing them, and stopping did not increase heart disease or death. [9]
  • Diabetes, smoking, and high blood pressure greatly increase heart-disease risk, and reducing those risks lowers heart disease; LDL has only a tiny effect and may even be harmful.
  • The U.S. has the most aggressive LDL targets anywhere; no other country sees this as necessary, yet the AHA keeps pushing levels lower even though lower levels are associated with higher mortality.
  • Lupus can carry about a 50-fold higher heart-disease risk, and the excess risk comes from inflammation, not cholesterol. [10]
  • Rheumatoid arthritis carries about 1.5-times higher mortality.
  • The main priorities are stopping smoking, eliminating diabetes through diet, and monitoring and controlling high blood pressure; cholesterol has much less importance.
  • Statins are relatively safe but still have side effects and costs, so their use depends on the magnitude of cholesterol risk and the larger risks that can be changed.

References

  1. [00:24] 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia — https://doi.org/10.1161/CIR.0000000000001423
  2. [01:25] Implications of the 2026 Dyslipidemia Guideline for Primary Prevention Statin Therapy — https://doi.org/10.1001/jama.2026.11246
  3. [02:50] Development and Validation of the American Heart Association's PREVENT Equations — https://doi.org/10.1161/CIRCULATIONAHA.123.067626
  4. [07:24] Global, regional and national trends in statin utilisation in high-income and low/middle-income countries, 2015–2020 — https://doi.org/10.1136/bmjopen-2022-061350
  5. [09:14] Association of Lipid, Inflammatory, and Metabolic Biomarkers With Age at Onset for Incident Coronary Heart Disease in Women — https://doi.org/10.1001/jamacardio.2020.7073
  6. [11:01] Global Effect of Modifiable Risk Factors on Cardiovascular Disease and Mortality — https://doi.org/10.1056/NEJMoa2206916
  7. [12:46] Global Effect of Cardiovascular Risk Factors on Lifetime Estimates — https://doi.org/10.1056/NEJMoa2415879
  8. [16:10] Association between low density lipoprotein and all cause and cause specific mortality in Denmark: prospective cohort study — https://doi.org/10.1136/bmj.m4266
  9. [18:11] Discontinuation of statins for primary prevention of atherosclerotic cardiovascular disease in adults aged 75 years or older (SAGA/SITE): a multicentre, open-label, pragmatic, non-inferiority randomised trial — https://doi.org/10.1016/j.lanhl.2026.100884
  10. [19:28] Age-specific incidence rates of myocardial infarction and angina in women with systemic lupus erythematosus: comparison with the Framingham Study — https://doi.org/10.1093/oxfordjournals.aje.a009122
 

Anita Breeze, The Ketogenic Woman, to talk all things carnivore weight loss, what changes as we get older, and what actually works when the scale just won’t move.

We talk about Anita’s incredible weight loss journey, the lessons she’s learned along the way, common mistakes that can stall fat loss, protein and fat, getting older, breaking through plateaus, and why your approach may need to change over time.

generated summary

Weight loss after 50

  • Weight loss after 40 is possible; hormones around perimenopause and menopause can make it harder, and substantial weight loss can still occur after menopause.
  • Anita has lost about 150 pounds overall, with normal fluctuations around that number, without counting temporary lows as additional weight loss.

From low carb to carnivore

  • About 15 years ago Anita started with Dr. Atkins: meat, about two cups of vegetables a day, and 20 net carbs while tracking; roughly 80–100 pounds were lost in that first low-carb period.[1]
  • After her father died in 2017, about 40–50 pounds returned, followed by a move into keto; for years the total loss moved between roughly 80 pounds and just over 100 pounds.
  • Keto was easy to follow, but frequent keto sweets carried food addiction into the diet; 30-day carnivore challenges gradually shifted eating toward meat, with about four years as a carnivore.
  • Removing foods such as nuts and almond flour helped produce roughly another 50 pounds of loss, and simple meals such as steak on a plate became preferable.
  • Strict carnivore eating is not necessary all the time: seasonings, an occasional pickle, or a keto-style celebration dessert can fit because the diet has to remain sustainable for life.

Protein, fat, and dairy

  • Close tracking is no longer used, but at age 68 protein gets more attention, with a target of about 120 grams a day and "protein first" even when the target is missed.
  • No single fat-to-protein ratio has worked permanently: high-fat, low-fat, and middle-ground carnivore have each worked for a period and then stabilized, while high fat improved mood without breaking the weight stall.
  • During a 31-day dairy-free August experiment, body weight stayed roughly within a two-pound range while waist size fell by three inches; whether the change was body fat, bloating, or something else is unknown.
  • Dairy can make this way of eating much easier to sustain, so permanent "never again" rules are not used; occasional dairy will continue to be tested for individual effects.

Ageless living, muscle, and daily habits

  • Carnivore for Ageless Living has more than 120 recipes, with a blueprint for simplifying life through morning light, movement, stress management, sleep, circadian rhythm, community, and small intentional habits.
  • Weight training currently occurs twice a week and previously occurred three times a week; for people over 50, maintaining or rebuilding muscle is a major priority.
  • Sarcopenia is a real problem in older adults, and severe muscle loss was common among nursing-home residents eating soups, puddings, cookies, and too little protein.
  • Maintaining muscle requires enough protein, and rebuilding lost muscle requires resistance exercise as well; declining appetite with age can make getting 120-plus grams of protein harder.
  • Sleep also needs deliberate attention with age, and resistance training helps with bone strength and protection when falls happen.
  • Hal Cranmer runs assisted-living homes using ketogenic and carnivore-style food, movement, and individualized care, and some residents have improved enough to return home.[2]
  • Vascular dementia in Anita's mother made brain health personally important; heart and metabolic health are linked with brain health, with omega-3-rich foods, B vitamins, folate, and vitamin D prioritized, and vitamin D supplementation used after testing showed a low level.
  • Creatine for brain health remains an area for further investigation, without enough evidence reviewed to speak confidently about it.

Sardine fasting and regular sardines

  • A sardine fast is not mainly a weight-loss tool; Dominic D'Agostino's sardine-fasting approach uses sardines to create a large energy deficit while still providing dense nutrition.[3]
  • Sardines strongly suppress appetite and provide omega-3s and dense nutrition, with perceived benefits for brain and joint health.
  • After the first few sardine challenges, Anita's knee pain improved enough to leave the replacement-surgery waiting list, although severe arthritis remained and a later fall caused more damage.
  • Courtney's own sardine fast clarified hunger versus emotional eating; she lost a few pounds, ketones rose, glucose fell, and calorie intake was probably very low on some days.
  • A sardine challenge is not required: sardine pâté and other recipes can be eaten regularly, and mixing sardines with foods such as tuna is an easier way to keep them in the diet.

References

  1. [01:56] Dr Atkins New Diet Revolution — https://www.penguin.co.uk/books/342511/dr-atkins-new-diet-revolution-by-atkins-dr/9780091889487
  2. [21:54] Revolutionizing Assisted Living: Hal Cranmer's Ketogenic & Carnivore Approach to Senior Wellness — https://www.metabolicmind.org/resources/news-views/podcasts/metabolic-mind-podcast/revolutionizing-assisted-living-hal-cranmers-ketogenic-carnivore-approach-to-senior-wellness/
  3. [25:27] Dr. Dominic D’Agostino — All Things Ketones, How to Protect the Brain and Boost Cognition, Sardine Fasting, Diet Rules, Revisiting Metformin and Melatonin, and More (#825) — https://tim.blog/2025/09/03/dr-dominic-dagostino-all-things-ketones/
 
view more: next ›